Perimenopause & your brain
How Do I Know I'm in Perimenopause?
Early signs can be subtle. Your cycle history, symptoms and overall health tell a more useful story than one hormone result.
Published October 13, 2026
Medically Reviewed
Medically reviewed by Amarish Dave, DO
Board-Certified Neurologist
Last medically reviewed: October 13, 2026
What Is Perimenopause?
Perimenopause is the transition leading up to menopause, when ovarian hormone production becomes more variable. Estradiol can rise and fall unpredictably rather than declining smoothly. Ovulation becomes less consistent over time, changing progesterone patterns too. These shifts can affect cycles and symptoms, but each woman’s experience is different.
Menopause is identified retrospectively after 12 consecutive months without menstruation when there is no other explanation. Pregnancy, medication and medical conditions can also stop periods. Hormonal contraception can obscure bleeding patterns, so the definition needs clinical context rather than simply counting months.
What Are the Earliest Signs of Perimenopause?
Early signs of perimenopause may include shorter or longer cycles, less predictable periods, hot flashes, night sweats and disrupted sleep. Some women notice increased anxiety, mood changes, difficulty concentrating, subjective brain fog, changing migraine patterns or vaginal dryness and discomfort. Symptoms may come and go rather than follow a steady progression.
No individual symptom diagnoses perimenopause. Brain fog after poor sleep, for example, may have several explanations. Consider the pattern over time: what changed, when it began, how it relates to your cycle and whether it interferes with daily life. The absence of hot flashes does not settle the question either.
Can You Be in Perimenopause With Regular Periods?
You can experience symptoms associated with hormonal fluctuations while still having regular periods. Normal-looking cycles do not mean hormones are identical from month to month. However, symptoms alone do not always establish that the formal menopausal transition has begun.
Reproductive-aging staging relies heavily on menstrual patterns. Persistent changes in cycle length help identify the early transition; longer gaps between periods characterize later stages. Symptoms can precede those recognizable changes. Perimenopause with regular periods therefore deserves a careful conversation, not an automatic diagnosis or dismissal. Our perimenopause brain-fog guide explores symptoms in this context.
What Age Does Perimenopause Usually Start?
The transition commonly begins during the 40s, although timing varies. There is no birthday when every woman enters perimenopause, and symptoms may evolve over several years. Family history, health and reproductive history can help a clinician interpret changes.
Symptoms or menstrual changes before age 40 deserve careful assessment for other causes and possible premature ovarian insufficiency. This is not something to diagnose from symptoms or an online checklist. Changes between ages 40 and 45 may also warrant a different assessment than those in otherwise healthy women over 45.
Why Can Perimenopause Affect the Brain?
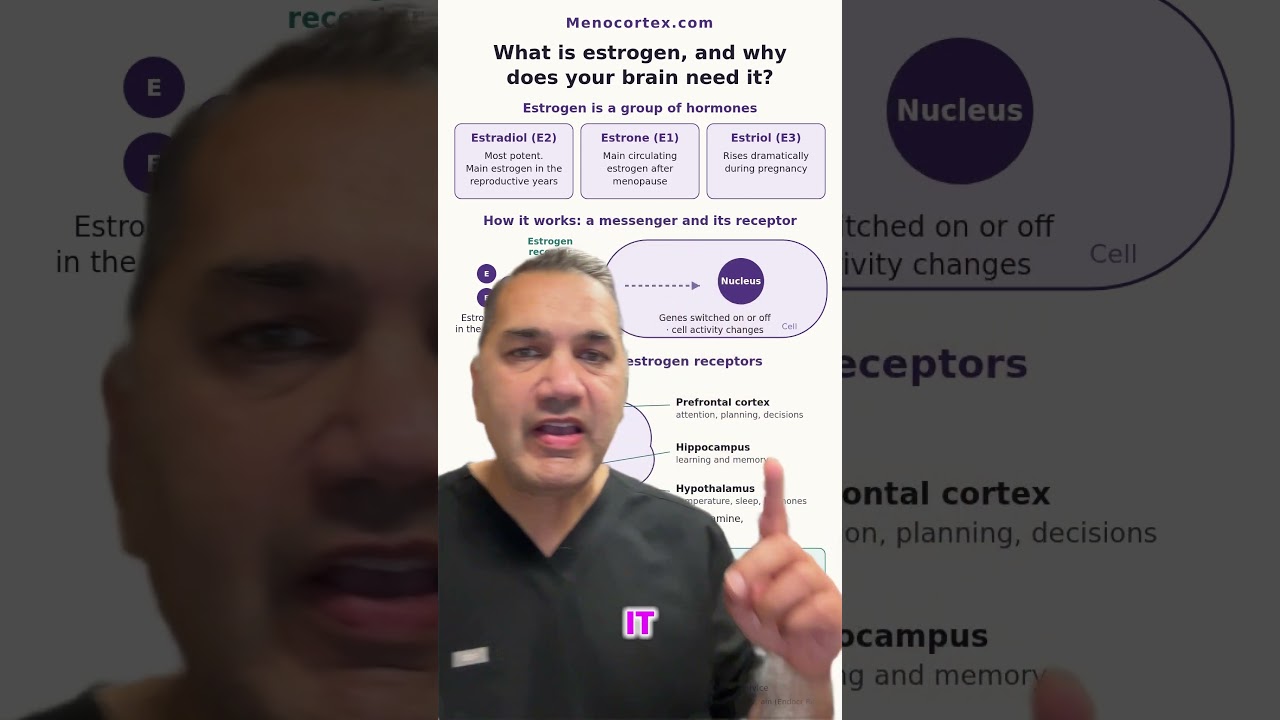
Ovarian hormones interact with neurological systems involved in sleep, thermoregulation, attention, working memory, mood, stress responses and migraine susceptibility. Estrogen signaling occurs in the hypothalamus, which helps regulate temperature and sleep; the hippocampus, involved in memory; and the prefrontal cortex, which supports attention and planning.
These biological connections do not prove that every neurological symptom comes from estrogen deficiency. Sleep disruption, stress and other conditions can contribute. Explore estrogen and the brain, menopause brain fog, menopause anxiety and migraine during perimenopause for more detail.
How Is Perimenopause Diagnosed?
For many otherwise healthy women aged 45 or older, clinicians recognize perimenopause from menstrual history, symptoms and clinical context rather than a single hormone test. They also consider medications, contraception, prior surgery and other explanations for changing periods.
FSH and estradiol can vary substantially from day to day. A normal result does not necessarily exclude the transition, and one abnormal result does not explain every symptom. Testing may be appropriate in younger women or when another condition is suspected. Perimenopause hormone testing should answer a specific clinical question, not substitute for an assessment.
What Else Can Look Like Perimenopause?
Thyroid disease, pregnancy, iron deficiency or anemia, sleep disorders, depression, anxiety disorders and medication effects can overlap with perimenopause symptoms. Other gynecological or endocrine conditions can change bleeding patterns. More than one contributor may be present at the same time.
Persistent, concerning or atypical symptoms deserve evaluation rather than being attributed automatically to hormones. Our thyroid symptoms versus menopause page explains one important overlap. A clinician can decide whether your history calls for targeted testing.
When Should You See a Doctor?
Seek medical evaluation for heavy or prolonged bleeding, bleeding between periods, new or worsening neurological symptoms, significant mood symptoms or signs of another medical condition. Bleeding after menopause also needs evaluation. Do not assume a new problem is harmless because you are in midlife.
Pregnancy remains possible during perimenopause until fertility has ended. Discuss contraception when relevant; irregular cycles do not reliably indicate infertility. Sudden weakness, difficulty speaking or a sudden severe headache require emergency attention, not a routine menopause appointment.
What Can Help During Perimenopause?
Tracking cycles, symptoms, sleep and migraine patterns can make appointments more useful. Consistent sleep habits, regular exercise and recognizing personal migraine triggers can support wellbeing. Hot flashes and night sweats may disrupt sleep and deserve discussion too.
Treatment depends on the symptom being addressed and your medical history. Individualized discussions may include hormonal or nonhormonal options, but no single treatment suits everyone. The goal is to understand what is happening, assess other causes and choose appropriate care—not to treat a hormone number in isolation.
Related videos


Share this page
Send this page to someone who may find it helpful.
Learn more about the neurological effects of perimenopause and menopause at MenoCortex.com. Subscribe to the MenoCortex YouTube channel and join the MenoCortex newsletter for evidence-based information about menopause and brain health.
Join The MenoCortex BriefJoin The MenoCortex Brief
Get exclusive menopause and brain-health videos, my weekly neurologist's take on new research, practical insights, and subscriber-only tools.Evidence-based information about menopause and brain health, from a neurologist's perspective.
Free. Unsubscribe anytime. Educational information only. Privacy Policy.
References & further reading
- 1.Patient guidance on perimenopause, menopause and hormone therapy — American College of Obstetricians and Gynecologists
- 2.MenoNote patient resources on menopause symptoms and treatment — The Menopause Society
- 3.Menopause: identification and management — recommendations — NICE guideline NG23
- 4.Executive summary of STRAW+10: staging reproductive aging — Menopause · consensus staging framework